Category: Features

  • The Borrowed Years: Why Britain’s Ageing Population Is Living Longer But Suffering More

    The Borrowed Years: Why Britain’s Ageing Population Is Living Longer But Suffering More

    There is something almost cruel in the headline. Life expectancy is up. Britain is ageing. People are living into their eighties and beyond in record numbers, and somewhere along the way this became a thing we were supposed to celebrate. But strip back the numbers, look at what the ONS actually publishes, and a far darker picture emerges. The years are there. The health, increasingly, is not.

    The UK healthy life expectancy decline is not a projection, not a worry for 2040. It is happening now, quietly and systematically, inside the bodies of millions of people who technically remain alive but who have not felt well in years. I find that genuinely unsettling, in a way that a simple death statistic never quite manages.
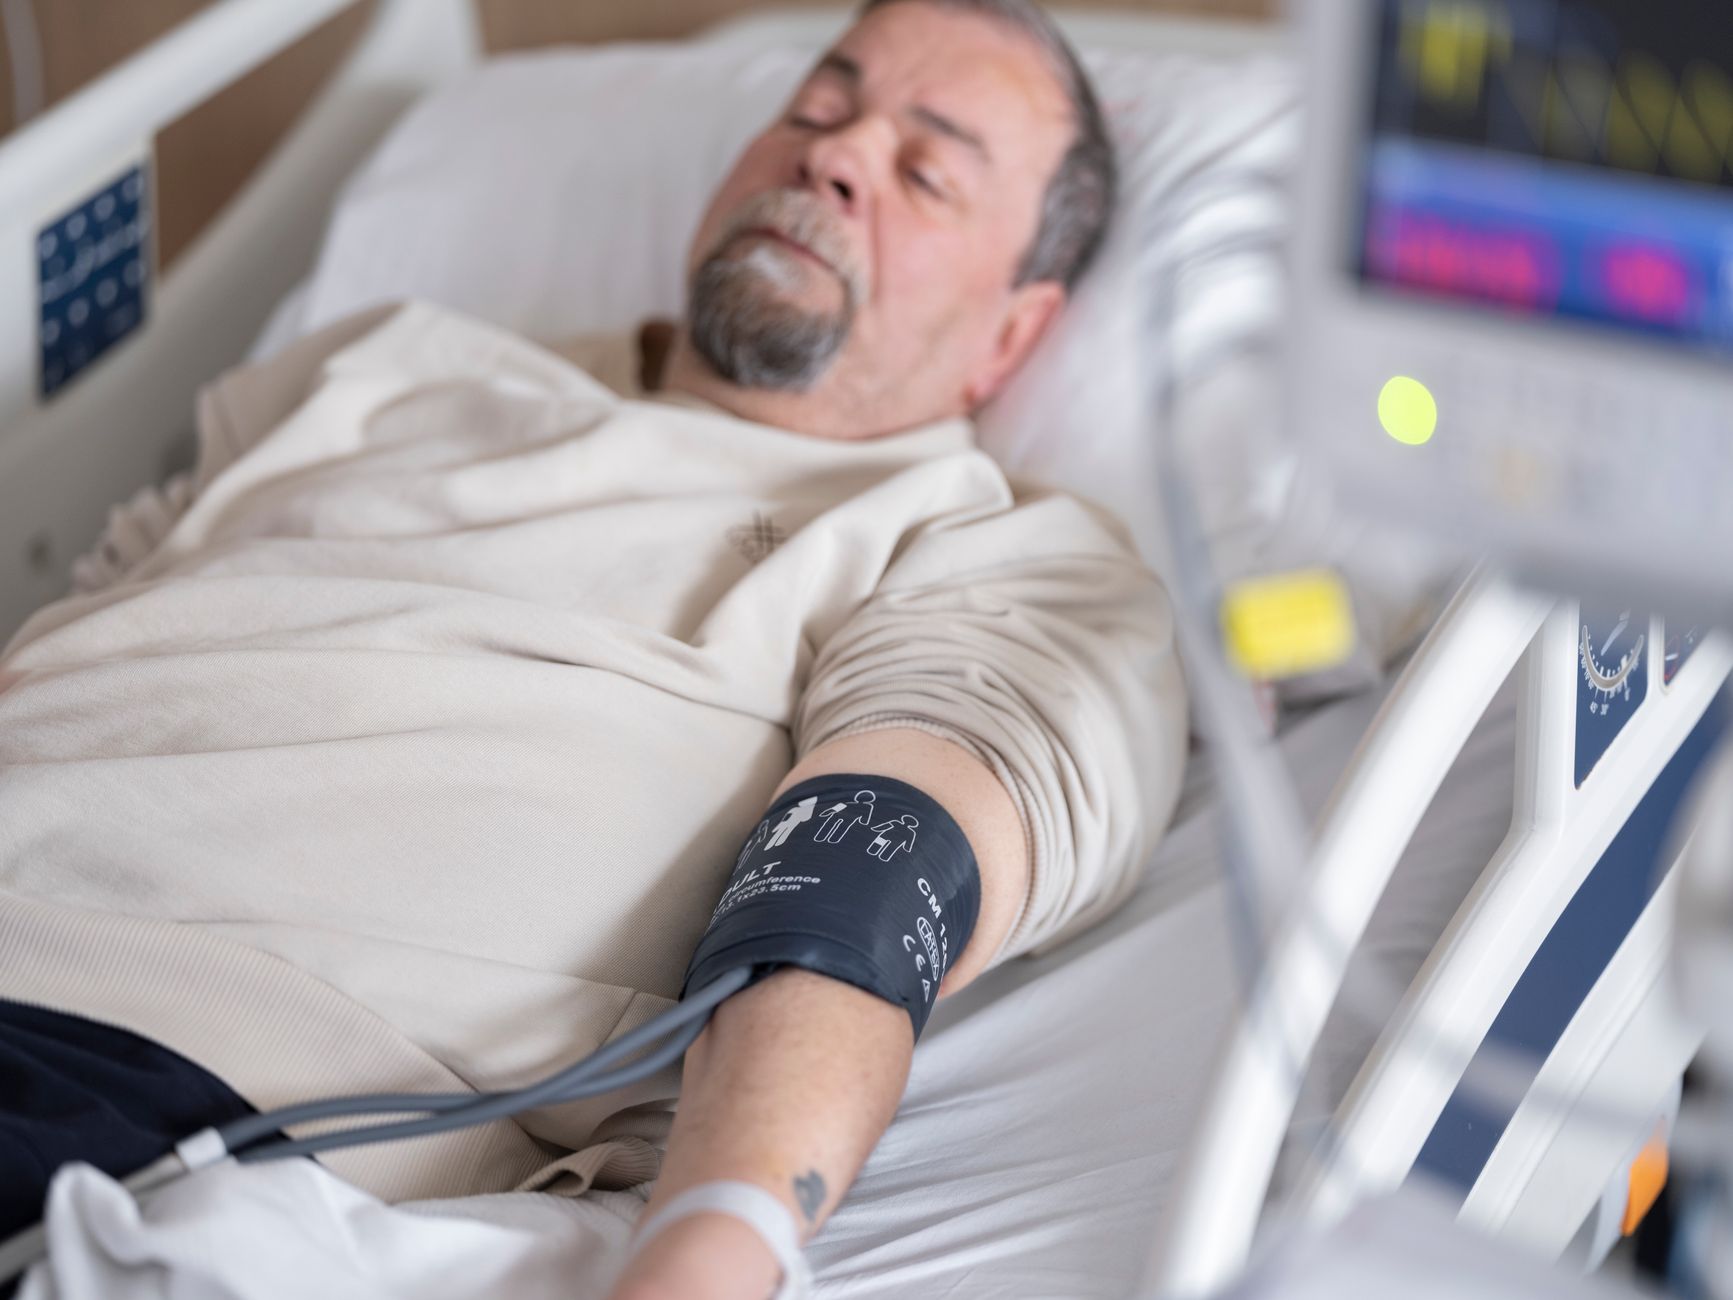
    Elderly patient in hospital ward reflecting the reality behind UK healthy life expectancy decline
    Photo by Engin Akyurt on Pexels

    What the ONS figures actually say

    According to the Office for National Statistics health state life expectancies bulletin for 2020 to 2022, a boy born in the UK can expect to live to around 78.6 years. A girl, to around 82.6. Those are the headline numbers. The ones that get cited, shared, used to suggest progress.

    But healthy life expectancy, defined as the number of years a person can expect to live in “very good” or “good” health, tells a different story entirely. For men, that figure sits at approximately 62.5 years. For women, 63.1. The gap between total life expectancy and healthy life expectancy is therefore roughly 16 years for men and nearly 20 years for women. Two decades, in a woman’s case, spent navigating a body that is working against her. That is not a rounding error. That is a generation of compromised living.

    What those extra years actually look like

    I think people imagine old age as a slow fade, a gradual dimming. The reality, for a substantial portion of the British population, is far more punishing. The NHS long-term conditions data shows that by the time someone reaches their late sixties, the probability of managing at least one chronic condition, whether that is type 2 diabetes, cardiovascular disease, chronic obstructive pulmonary disease, or musculoskeletal pain, is extremely high. By their mid-seventies, many are carrying two or three simultaneously.

    These are not background inconveniences. Chronic pain limits mobility. Cognitive decline erodes independence. Heart failure means entire days organised around breathlessness and fatigue. The NHS currently has around 15 million people in England living with one or more long-term conditions, a figure that consumes around 70 per cent of the NHS budget and continues to grow. That is the real texture of those borrowed years.

    Why healthy life expectancy is falling behind

    Several forces are pulling in the same direction, and none of them are cheerful. Ultra-processed food has restructured British diets in ways that accelerate metabolic disease. Physical inactivity, particularly stark in deprived areas, compounds it. The collapse of preventative care, hollowed out through years of NHS pressure and understaffing, means conditions that might once have been caught and managed early are instead presenting late, badly, with complications already established.

    There is also the inequality dimension, which the ONS data lays bare with particular bleakness. A man living in Blackpool has a healthy life expectancy roughly 19 years lower than a man in the London borough of Richmond upon Thames. Same country. The same NHS in name. But those two men are ageing inside entirely different biological realities, shaped by income, air quality, housing, stress, and access to care. The UK healthy life expectancy decline is not evenly distributed. It falls heaviest on those who already have least.

    The sleeplessness connection nobody talks about

    One thread worth pulling at is how chronic illness and poor sleep form a feedback loop that accelerates physical deterioration. Persistent pain disrupts sleep. Disrupted sleep worsens inflammation, impairs immune function, and raises cardiovascular risk. I wrote about this dynamic recently in a piece on the dark science behind Britain’s worsening insomnia epidemic, and what struck me most was how many of the people worst affected are older adults already managing long-term conditions. The body becomes a system of compounding failures. Each problem makes the others harder to bear.

    The ecosystem around us is also declining

    There is a wider, stranger resonance to all of this too. The degradation of human health does not happen in isolation. Britain’s natural environment is under simultaneous pressure, its biodiversity collapsing in ways that affect air quality, mental health, and the basic psychological restoration that green space provides. I explored some of that in an earlier piece on what Britain’s collapsing biodiversity actually looks like, and there are uncomfortable parallels: systems that look intact from a distance, quietly failing from within.

    Who carries the weight of these borrowed years

    The practical consequences fall on a relatively small number of people. Informal carers, most of them women, most of them in their forties and fifties, who reduce their own working hours or abandon employment entirely to look after ageing parents. The NHS, already operating under structural strain. And the individuals themselves, who perhaps expected retirement to look like something other than a slow negotiation with their own decline.

    There is a cultural silence around this. We speak freely about living longer. We do not speak as readily about what it means to be bedridden at seventy-four, or to lose the ability to leave your terraced house unassisted at seventy-one. The language around ageing in public discourse is relentlessly optimistic, full of active retirees and grey travellers. That is not wrong, exactly, but it is incomplete to the point of distortion.

    Is anything being done about it

    The government’s NHS Long Term Plan identified prevention as a priority, and there are genuinely promising programmes around early intervention for cardiovascular disease and diabetes. But the structural conditions that drive poor health, poverty, inadequate housing, food insecurity, are not medical problems with medical solutions. The pattern of things being quietly shelved in British public life applies here too, in a way. Prevention is underfunded precisely because its successes are invisible, while its costs are immediate.

    What the ONS data tells us, without sentiment, is that Britain is producing more years of human life while producing fewer years worth living fully. The borrowed years are real. They cost something. And right now, the people spending them are largely paying that cost alone.


  • Named and Forgotten: The Unsolved Murders That British Police Have Quietly Shelved

    Named and Forgotten: The Unsolved Murders That British Police Have Quietly Shelved

    There is a list. It doesn’t trend on social media. Politicians don’t wave it about in the Commons. But it exists, quietly damning, running to hundreds of names across England and Wales, people who were killed, whose killers were never found, and whose cases have been downgraded, deprioritised, or simply left to gather dust in a filing system that moves on without them. Unsolved murders UK cold cases are not an anomaly. They are a pattern. And the pattern has a shape that should disturb anyone willing to look at it.

    I’ve spent time reading through the Home Office homicide statistics and cross-referencing them with charity records, campaign group reports, and old news coverage. What emerges is not a picture of overworked but well-meaning constabularies doing their best. It’s something grimmer than that. It’s a system where the resources allocated to a murder investigation, and the longevity of that investigation, correlate strongly with factors that have nothing to do with justice.

    Rain-soaked police cordon tape on a British street, evoking unsolved murders UK cold cases
    Photo by James Collington on Pexels

    How many unsolved murders are there in England and Wales?

    The honest answer is that nobody publicises a clean number, which is itself telling. The Home Office records homicides and their outcomes, but “outcome” doesn’t always mean conviction. According to published figures, somewhere between 100 and 200 homicides recorded each year in England and Wales result in no suspect being charged. Over a decade, the accumulation runs into the thousands. The charity Murdered Abroad and UK-focused cold case researchers have consistently estimated that around 1,000 murders from the past 30 years remain unsolved in England and Wales alone. Some families have been waiting since the 1980s.

    What makes this especially uncomfortable is how selectively the machinery of investigation operates. Major incident rooms are expensive. A single murder investigation can cost a constabulary upwards of £1 million in the first year. When budgets tighten, something gives, and what gives, historically, is the cases that generated the least media heat when they first occurred.

    The geographic lottery of getting justice

    Where you are killed in England and Wales partly determines whether anyone keeps looking for the person who killed you. Forces like the Metropolitan Police, with its specialist Homicide and Major Crime Command, have dedicated cold case review units. Others, particularly underfunded regional constabularies in post-austerity Britain, do not. A murder victim in a rural part of the East Midlands or South Wales may have their case reviewed only if a journalist asks awkward questions, a new witness surfaces, or DNA technology finally catches up.

    The postcode lottery of British public services, familiar from NHS waiting times and school provision, extends here into something far more final. It extends into whether the state will keep trying to name and punish the person who ended someone’s life. This is not a conspiracy. It is something more insidious: structural indifference dressed up as resource management.

    Who gets forgotten: the bias baked into cold cases

    The uncomfortable truth, documented by researchers and campaigners for years, is that certain categories of victim are systematically less likely to have their cases pursued long-term. Street sex workers. Drug users. Young Black men killed in areas written off as “gang-related”. People with mental illness. Rough sleepers. The pattern holds across the data. When a victim’s life is deemed complicated, when their death fits a narrative that press and public find easy to dismiss, the investigation’s urgency fades faster.

    I’d argue this is not a new observation, but it remains a buried one. The Femicide Census, which tracks female homicides in the UK, has repeatedly shown that women killed by partners or ex-partners in lower-income households receive substantially less sustained investigative attention than cases that attract media sympathy. Meanwhile, the families of young Black men killed in London speak of a wall of near-silence after the initial flurry of activity. Some of those cases are now a decade old with no charge ever made.

    The murdered, in these instances, are named. That is the grim minimum the state offers. Named, and then quietly forgotten.

    Cold case review units: the promise and the reality

    Britain does have cold case review infrastructure. The National Crime Agency supports some reviews. Forces with capacity run their own units. Advances in forensic genealogy, the kind of DNA matching that cross-references crime scene samples with genealogy databases, have produced breakthroughs in cases that seemed permanently closed. The 2019 identification of a suspect in a decades-old Nottinghamshire murder through such techniques showed what is possible. So did several cases in the late 2010s where old crime scene exhibits, re-tested with low-copy number DNA analysis, produced first-time identifications.

    But these are exceptions, not a system. Cold case review is largely reactive, triggered by new evidence or external pressure, rather than a methodical re-examination of old failures. There is no national register of unsolved murders that is publicly accessible, no mandatory review cycle, no statutory obligation on forces to revisit cases after a set period. Families who want to know what happened to their loved ones must often do their own digging, hire private investigators, lobby MPs, and petition police and crime commissioners. The burden falls on the bereaved.

    The same quiet systemic neglect that shapes how Britain abandons things it cannot see operates here, too. When something ceases to be visible, it becomes easier to let it decay. Cold cases are invisible almost by definition.

    What families are left with

    I think about what it must be like to know someone killed your child, your mother, your brother, and to watch a system shrug. Not dramatically. Not cruelly, as a conscious act. But shrug, nonetheless, as funding cycles change and senior investigating officers move to other cases and the file sits somewhere unread. The sleep that evades Britain’s bereaved in these circumstances is not simply grief; it is a specific, unresolvable kind of torment that has been documented in research on families of unsolved homicide victims. For more on what chronic distress of this kind does to the body and mind, the work around Britain’s sleep crisis is relevant in ways most people don’t connect.

    The families of the named and forgotten are not asking for miracles. They are asking for a system that does not decide, on the basis of postcode, media interest, or the perceived social value of a victim, whether a human death is worth continued pursuit. That is not an unreasonable request. It is the minimum a just society owes its dead.

    The list exists. It is long. And every year, it gets longer.

  • The Quiet Apocalypse: What Britain’s Collapsing Biodiversity Actually Looks Like Up Close

    The Quiet Apocalypse: What Britain’s Collapsing Biodiversity Actually Looks Like Up Close

    There is a particular kind of silence that unsettles you before your brain can name why. I felt it last spring, standing at the edge of a chalk meadow in Wiltshire that my grandfather used to describe as alive with sound. Bees so thick in the clover you could feel their weight on the air. Lapwings cartwheeling overhead. The rasp of grasshoppers underfoot. None of it was there. The field was green. The sky was blue. But something had been subtracted from the world, quietly, without announcement, and what remained felt like a stage set with no actors and no audience.

    That is what UK biodiversity collapse 2026 actually looks and feels like from the ground. Not a disaster film. Not a headline. A subtraction. A slow, eerie evacuation of the living world that most people haven’t noticed yet because it has happened gradually enough to escape memory.

    An eerily empty English chalk meadow at dawn, capturing the silence of UK biodiversity collapse 2026
    Photo by Ludvig Hedenborg on Pexels

    What the numbers say, and what they don’t

    The ONS Natural Capital Accounts have been tracking the degradation of Britain’s ecosystems for years. By their own measures, the UK ranks among the most nature-depleted countries on earth. More than half of all species monitored since 1970 have declined in abundance. Around one in six is now threatened with extinction. Hedgerow length has shrunk by roughly a quarter since the 1980s. Freshwater invertebrate populations, the base of the food web in rivers and streams, have collapsed in many catchments across England and Wales.

    Numbers do not bleed, though. They don’t carry the weight of what is actually gone. The cuckoo, once the sound of an English spring so ordinary it became a cliché, has declined by 68 per cent since 1995. The turtle dove is close to functionally extinct on British soil. Corn buntings, tree sparrows, spotted flycatchers, birds that a generation ago would have seemed unremarkable, are now rare enough that a sighting warrants a note in a journal. The farmland bird index, which the RSPB uses as a broad proxy for rural ecological health, has halved since 1970 and has not recovered in any meaningful way.

    The coast is losing its voice too

    Walk a shingle beach in Kent or Suffolk in June and you might find yourself scanning for little terns. Small, frantic birds, bright white, that used to nest in loose colonies on the stones. Their numbers have been falling for decades. Disturbance, predation from increasing crow and fox populations, and coastal erosion driven by rising sea levels have all pressed in on them at once. I’ve spoken to wardens at Chesil Beach in Dorset who describe entire breeding seasons wiped out by a single high tide. What took tens of thousands of years to establish as a habitat is being unmade in a human lifetime.

    The seagrass meadows off the Welsh coast and in the Solent tell a similar story. These underwater grasslands once nursed juvenile fish, filtered sediment, and sequestered carbon at rates comparable to woodland. By some estimates, Britain has lost over 90 per cent of its seagrass since the early twentieth century. The water above a dead seagrass bed is clear and very still. Beautiful, in the way that an empty room is beautiful.

    Why the countryside feels haunted now

    UK biodiversity collapse 2026 is not just an ecological story. It is a perceptual one. Ecologists call it “shifting baseline syndrome”, each generation accepts the depleted world it inherits as the normal one. My grandfather’s chalk meadow is my baseline of loss. For someone born in 2010, the already-quieter countryside of their childhood is the standard against which further collapse will be measured. The ghost of what was there goes ungrieved because most people never knew it existed.

    This is not comfort. It is the mechanism by which an apocalypse can proceed without anyone declaring an emergency. The silence spreads. The baselines shift. The hedges thin. The moths stop arriving at lighted windows. The slow-worm under the garden slate is simply not there one year, and then not the year after that, and eventually the slate stops being lifted.

    There is a known link between ecological loss and human psychological health, a kind of ambient grief that researchers sometimes call solastalgia, the distress caused by watching your own environment deteriorate. Britain’s worsening sleep and mental health patterns are not disconnected from the world outside the window, however much we might prefer to believe they are. We are animals embedded in an ecosystem, even when we forget it.

    The pressures driving the collapse

    Agricultural intensification since the 1950s restructured the countryside at a pace nature had no mechanism to absorb. Pesticide use eliminated the insect base. Field margins vanished. Ancient hedgerows were grubbed out for efficiency. Then came the development pressure on brownfield and greenfield sites alike, the light pollution that disorients moths and disrupts nocturnal ecology, the plastic load in rivers, the nutrient runoff from agricultural land that turns slow rivers into green soup.

    The government’s post-Brexit Environmental Land Management scheme was supposed to redirect farming subsidies away from simple acreage payments toward genuine ecological outcomes. Progress has been slow, contested, and complicated by agricultural lobbying. Meanwhile, the targets set under the Global Biodiversity Framework signed at COP15 in Montreal, 30 per cent of land and sea protected by 2030, remain aspirational rather than operational for much of the UK. The machinery of protection moves at government speed. The collapse moves faster.

    What is left, and why it matters

    I don’t want to leave this purely as an inventory of loss, though the losses are real and the scale of UK biodiversity collapse in 2026 demands that they be named plainly. Because there are places where the reversal is happening. The Knepp Estate in West Sussex, rewilded over two decades, now carries turtle doves, purple emperor butterflies, and peregrine falcons. The beaver reintroductions on the River Otter in Devon have measurably altered hydrology and increased species diversity downstream. The seagrass restoration work in Pembrokeshire, led by Project Seagrass, has shown that given the chance, these habitats recover with startling speed.

    None of this cancels the scale of what has been lost. But the silence in my grandfather’s meadow is not inevitable. It was made. That means it can be unmade. The question is whether enough people hear it first.

  • Sleep No More: The Dark Science Behind Britain’s Worsening Insomnia Epidemic

    Sleep No More: The Dark Science Behind Britain’s Worsening Insomnia Epidemic

    There is something deeply wrong with the night in this country. Millions of people lie there, perfectly still, eyes fixed on ceilings they cannot see, listening to the hum of a city that never quite stops. The insomnia epidemic UK researchers and NHS clinicians have been documenting for years has not slowed. If anything, it has deepened, spread, and burrowed into demographics that once seemed immune, teenagers, young professionals, even children who should be dreaming of nothing more sinister than school corridors. I’ve read enough of the data now to find it genuinely unsettling. Not sad, not unfortunate. Unsettling.

    According to NHS England, roughly one in three people in the UK regularly experience insomnia symptoms. That’s approximately 22 million adults lying awake when they shouldn’t be. Not occasionally. Regularly. The NHS also reports that poor sleep is linked to a significantly elevated risk of heart disease, type 2 diabetes, obesity, and depression. When you stack those figures together, you stop thinking about insomnia as a lifestyle inconvenience and start thinking of it as a slow public health catastrophe unfolding in the dark.

    Person lying awake in a dark bedroom, reflecting the insomnia epidemic UK adults are experiencing
    Photo by Ron Lach on Pexels

    What the screens are doing to us

    The obvious villain is the one we already know about, and yet knowing hasn’t stopped us. Blue light emitted by phones and tablets suppresses melatonin production, the hormone that signals to the brain that darkness has arrived and rest should follow. What screens do, essentially, is lie to your biology. They tell your nervous system it is perpetually midday. Your body, confused and a little frantic, obliges.

    Ofcom’s 2025 communications report found that UK adults now spend an average of over four hours per day on their smartphones. A significant chunk of that happens in the hour before bed. The brain, having spent that hour absorbing social media conflicts, breaking news cycles, and the low-grade dread of an unanswered email, does not simply switch off the moment the phone hits the bedside table. It carries the static. I’ve noticed this myself on the nights I don’t put the phone away, that peculiar restlessness, the rehearsed arguments, the scrolling thoughts that feel borrowed from a feed rather than genuinely my own.

    The problem is structural. These platforms are engineered to resist disengagement. Every notification, every autoplay, every algorithm-fed outrage is a tiny hook keeping you tethered past the point where your body needs release. The insomnia epidemic UK clinicians are observing isn’t random misfortune. It is, in part, the biological cost of products designed to colonise your attention without limit.

    Urban noise and the city that never sleeps so you don’t either

    Beyond the screen, there is the city itself. Urban noise pollution in British towns is measurably worse than it was twenty years ago. The World Health Organisation classifies night-time noise above 40 decibels as damaging to sleep quality. On most major roads in London, Manchester, Birmingham, and Leeds, ambient night-time noise regularly exceeds that threshold. Sirens, lorries on their early morning runs, foxes, aircraft on holding patterns over Heathrow, these are not occasional disruptions. They are the ambient score of urban British life.

    Research published by the government’s own noise action planning documents acknowledges that road traffic noise alone disturbs the sleep of around 15 million people across England. That figure tends to be buried in planning consultations rather than treated as the health emergency it represents. There’s something grimly fitting about that: a problem that happens in the dark, largely ignored until the light comes up.

    Terraced houses and semi-detached properties, the dominant housing stock across most British towns and cities, share walls. Neighbours are not abstract. You hear their arguments, their late-night television, their insomnia. Sleep deprivation, it turns out, is mildly contagious in close-quarters living. One bad sleeper in a terrace can affect four households. I don’t think we talk about this enough.

    The psychological weight nobody names

    There is a third force operating beneath the screens and the noise, and it is harder to quantify. Call it ambient anxiety. The background radiation of modern British life, the cost of living, housing insecurity, the erosion of any sense that the future is predictable, creates a psychological state that is fundamentally incompatible with sleep. Sleep requires a degree of surrender. You have to let go of the day, trust the darkness, accept that tomorrow will sort itself.

    A nation that has watched its mortgage rates double in under three years, that has seen NHS waiting lists stretch past seven million people, that has absorbed a relentless stream of crisis-framing in its media, that nation is not in a surrendering mood at bedtime. The mind stays watchful. Vigilant. Ancient threat-detection circuitry, designed for genuinely dangerous environments, fires on problems it cannot resolve: debt, job security, an uncertain future. Sleep doesn’t stand a chance against that kind of internal noise.

    Clinical psychologists have a term for this state: hyperarousal. The nervous system stuck at a pitch that makes rest physiologically difficult. Cognitive behavioural therapy for insomnia (CBT-I) is now the NICE-recommended first-line treatment precisely because the problem is so often rooted in thought patterns and psychological states rather than anything physically wrong with the body. The NHS has increased availability of CBT-I through its Talking Therapies programme, though waiting times remain long and patchy across regions.

    The sleeping pill trap

    When rest becomes impossible, the temptation is to reach for a chemical solution. UK prescriptions for sleep medications have risen sharply over the past decade. Zopiclone, one of the most commonly prescribed short-term sleep aids, saw prescription volumes increase by over 30% between 2015 and 2023 according to NHS Business Services Authority data. The drugs work, in the short term, in the way a hammer works on a nail. But they suppress the deeper sleep stages the brain needs for emotional regulation and memory consolidation. You get unconsciousness. You don’t get rest. Not really.

    Long-term reliance on hypnotics creates its own darkness. Rebound insomnia upon withdrawal can be worse than the original condition. The insomnia epidemic UK prescribers are grappling with has a pharmaceutical shadow that rarely gets the same headlines as the epidemic itself.

    What rest actually looks like now

    I’m not going to tell you to drink chamomile tea and buy blackout curtains, though those aren’t bad ideas. The scale of this problem is too large for individual habit tips to carry. What I’d argue instead is that the insomnia epidemic UK adults are living through is a symptom of something structural: a culture that has decided productivity is the only legitimate use of time, that rest is laziness dressed up, that the night should be colonised like everything else.

    Reclaiming sleep means, at some level, resisting that. Treating darkness as something to be honoured rather than filled. The CBT-I approach asks you to rebuild an association between bed and sleep rather than bed and anxious wakefulness. That takes weeks. It is uncomfortable. It works better than pills, and the effects last. The NHS Talking Therapies service is the place to start if you’re struggling, not because I believe in easy fixes, but because the alternative is lying there every night, wide awake, listening to a city that has forgotten it needs to rest too.

    Britain’s insomnia problem has a lot of faces. Every one of them is exhausted.

    Frequently Asked Questions

    How widespread is the insomnia epidemic in the UK?

    NHS England estimates that around one in three UK adults regularly experience insomnia symptoms, equating to roughly 22 million people. The problem has worsened over the past decade, with NHS prescriptions for sleep medications rising significantly and GP consultations about sleep increasing year on year.

    What are the main causes of insomnia in the UK right now?

    The main drivers include excessive screen use before bed (which disrupts melatonin production), urban noise pollution from road traffic and city life, and a background of widespread psychological stress linked to financial pressures and housing insecurity. These factors often compound each other, making chronic insomnia difficult to resolve without addressing several causes simultaneously.

    What is CBT-I and is it available on the NHS?

    Cognitive behavioural therapy for insomnia (CBT-I) is the treatment approach recommended by NICE as the first-line option for chronic insomnia. It’s available through the NHS Talking Therapies programme (formerly IAPT), though waiting times vary considerably depending on where in the UK you live.

    Are sleeping pills a safe long-term solution for insomnia?

    No. Medications like zopiclone are intended for short-term use only and suppress the deeper sleep stages needed for emotional and cognitive recovery. Long-term use can lead to dependency and rebound insomnia, where sleep difficulties become worse when the medication is stopped. NHS guidance consistently recommends CBT-I over medication for ongoing insomnia.
